ClinicalEye: Finding the Right Views
for 3D CT Visual Question Answering
A training-free VLM agent that, like a clinician, uses anatomy to decide where to look in a CT volume — and how to arrange what it shows.
Overview
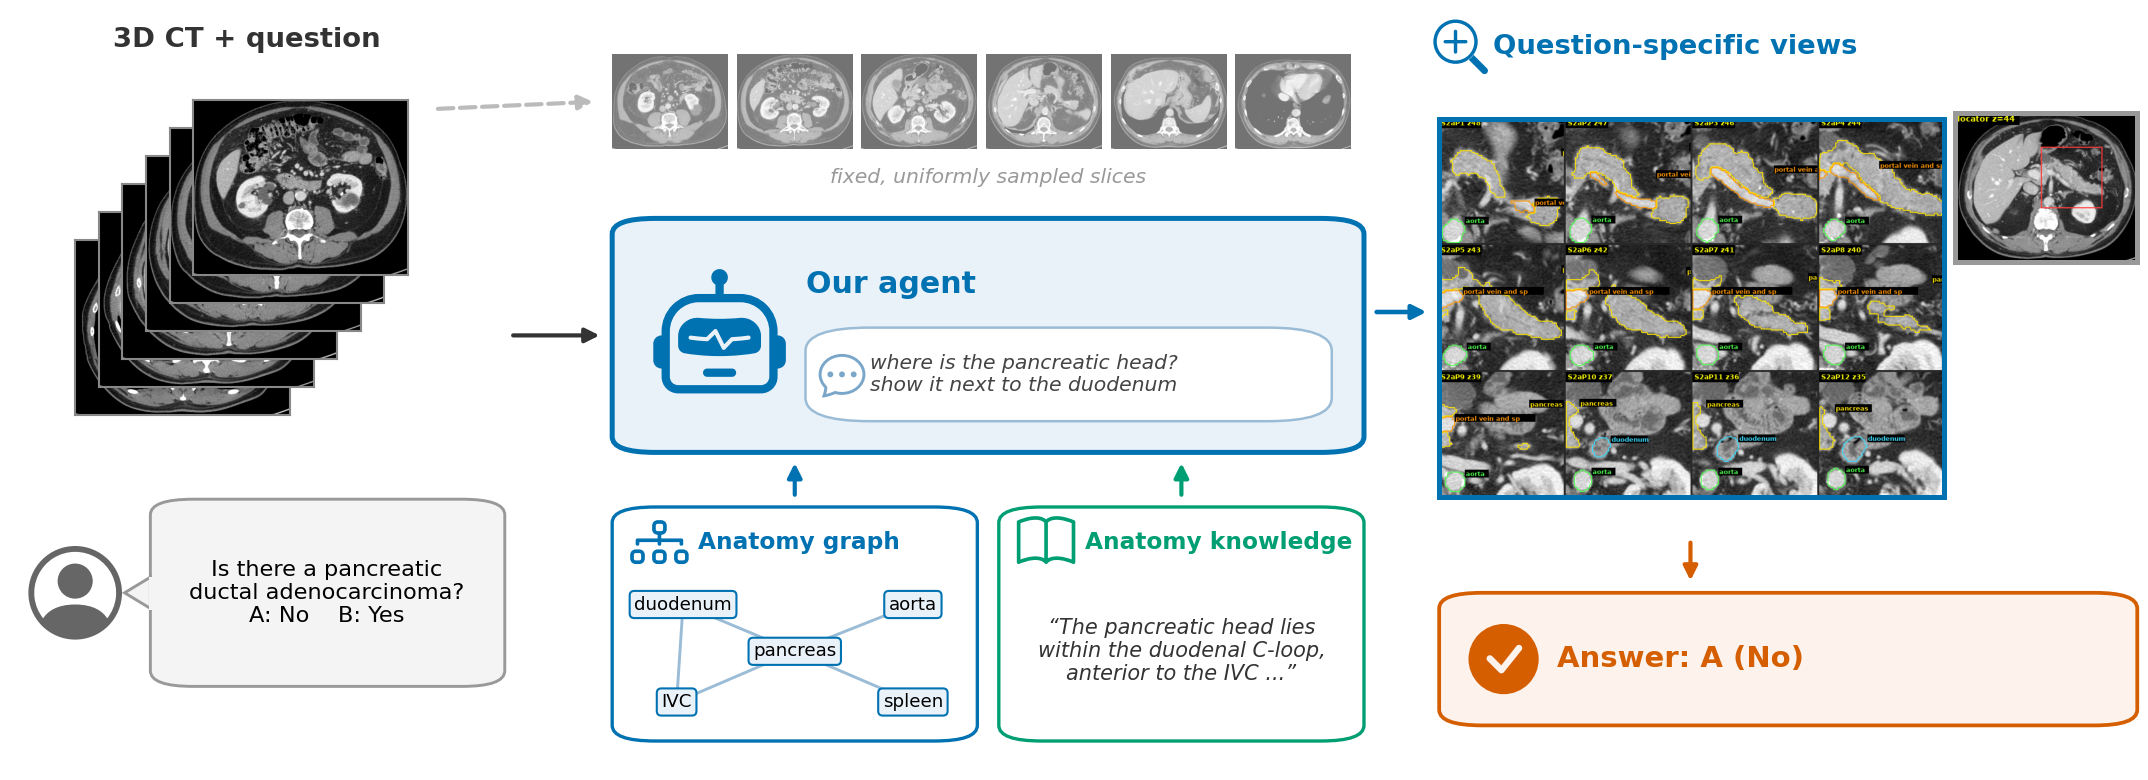
Vision-language models (VLMs) struggle with 3D CT: the volume has far more slices than fit into a prompt, and the relevant anatomy (a pancreatic head, a vessel next to a lesion) is often small and not marked. Clinicians solve this with anatomy: they know which structures to look at, where they are, and which views to put side by side. ClinicalEye gives a VLM the same two resources — an anatomy graph computed from automatic segmentation and a cited anatomy knowledge base — and splits the work between a reader that reasons about the question and a navigator that only locates anatomy and composes views.
Benchmark protocol
- No benchmark metadata reaches our agent: the reader starts with only the question, the answer options and the names of the segmented structures — no organ, lesion or question-type labels, and no images.
- All compared methods run on the same 903 questions (lite903, stratified over the 42 subtypes) with the same base models.
- One sample per condition; differences are tested with paired exact McNemar tests.
Method
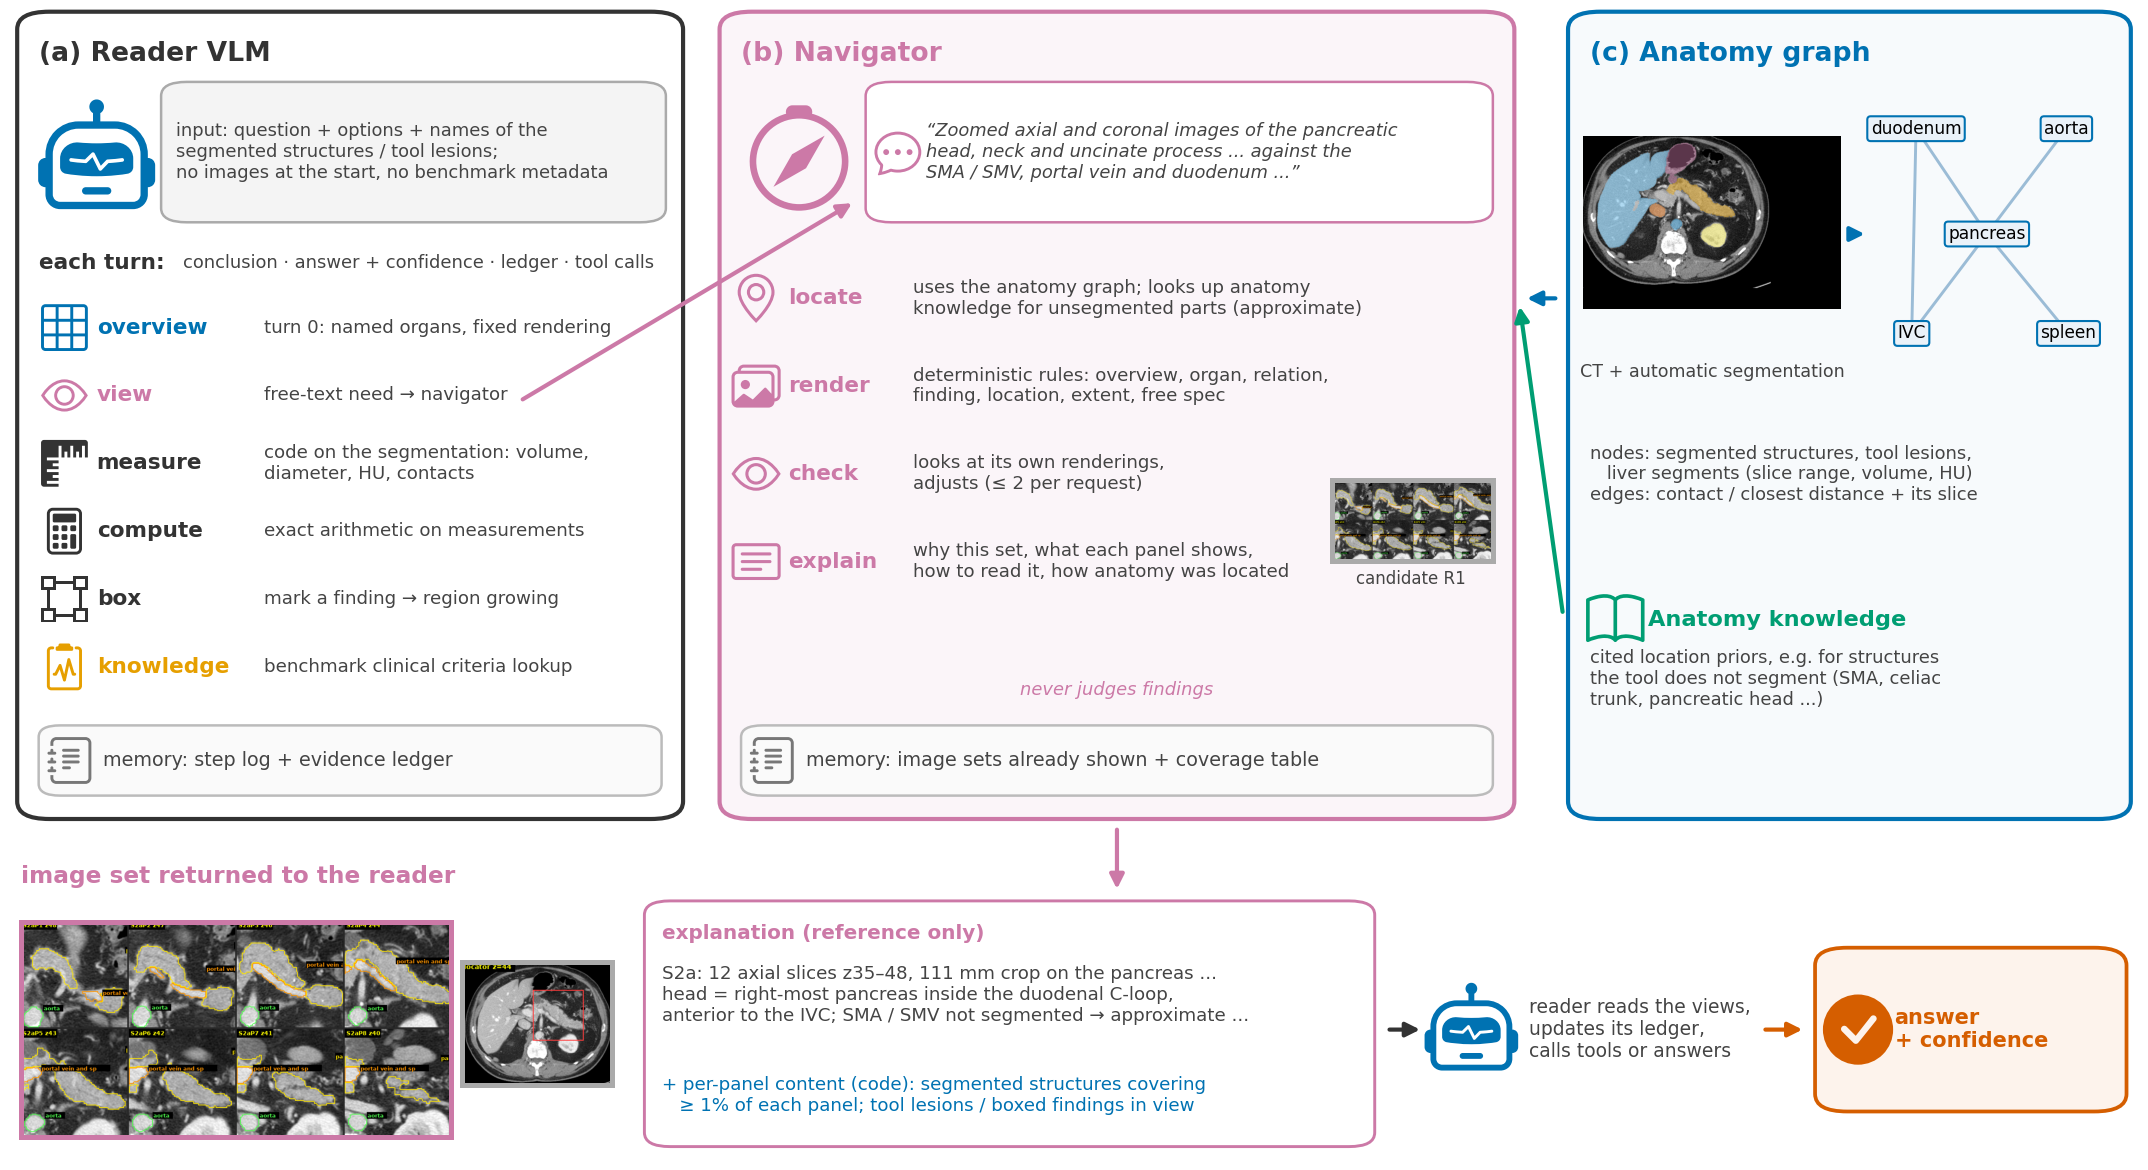
resource Anatomy graph
Built automatically from TotalSegmentator output.- Nodes: segmented structures, tool lesions and liver segments, each with slice range, volume and HU.
- Edges: contact / closest distance between structures, plus the slice where it occurs.
resource Anatomy knowledge
Not every clinically relevant structure has a sufficiently good tool. A cited knowledge base gives location priors for such structures (e.g. SMA, celiac trunk, pancreatic head/tail, CBD): vertebral level, relations, appearance on axial CT, and how to locate them from segmented neighbours.agent Reader VLM
Starts with no images. Each turn: step conclusion, current answer + confidence, evidence ledger, tool calls:overview— turn 0, named organs, fixed renderingview— a free-text need, sent to the navigatormeasure/compute/box— code on the segmentation (volume, diameter, HU, contacts; arithmetic; mark a finding)knowledge— benchmark clinical criteria lookup
agent Navigator VLM (never judges findings)
- Locate: anatomy graph (slice ranges, neighbour relations) + anatomy-knowledge lookup tool; unsegmented parts are marked approximate.
- Render with deterministic rules: overview, organ, relation, finding, location, extent, free spec (plane, slices, zoom/FOV, window, locator).
- Check its own renderings and adjust (≤2 per request).
- Explain: why this set, what each panel shows, how to read it, how the anatomy was located — plus code-computed per-panel content.
Trajectory viewer
Real episodes from the evaluation run, step by step. All texts are quoted from the logged episode files (long texts truncated with “...”); images are the renderings that were actually produced. S# = image sets delivered to the reader; R# = navigator candidate renderings.
Tip: use the ← / → keys to step through; click an image to enlarge.
Results
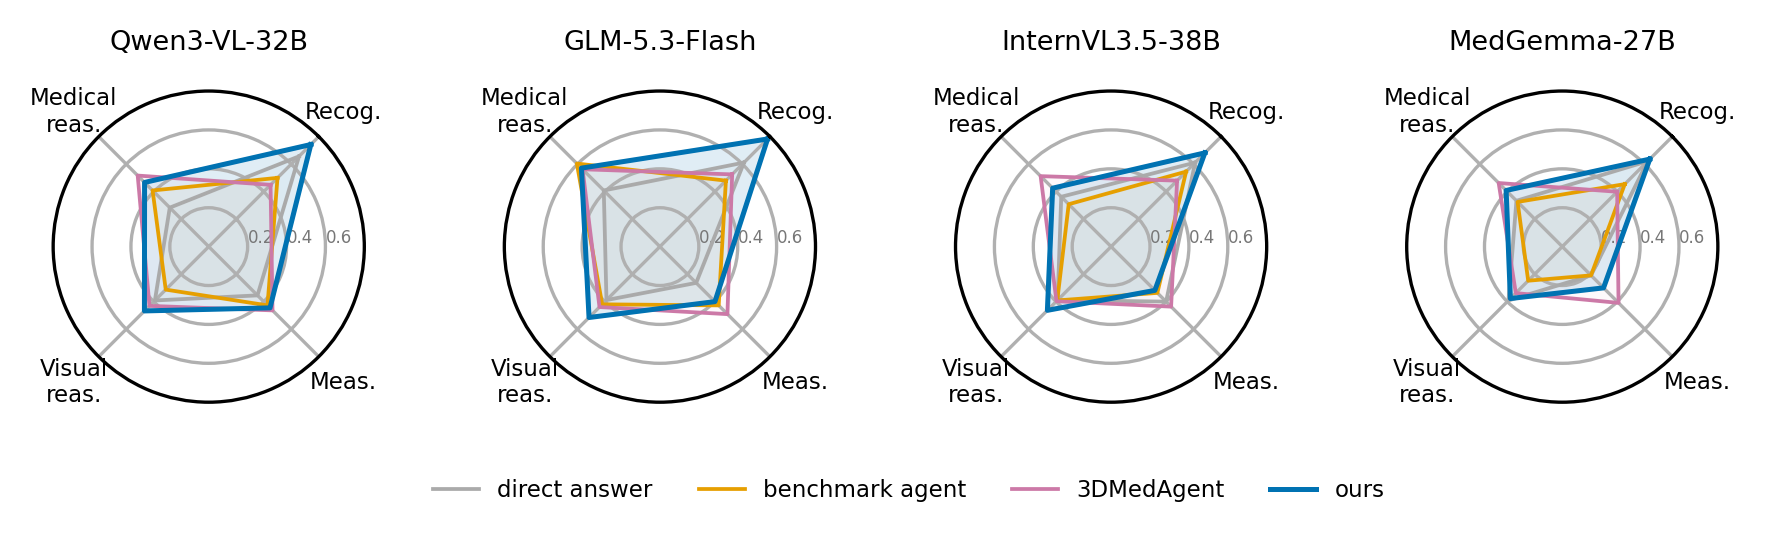
Accuracy on lite903 (903 questions, stratified over 42 subtypes), single sample per condition. Every column uses the same base model in each row.
| Base model | DeepTumorVQA | 3DMedAgent | Single call | ClinicalEye (ours) | ||
|---|---|---|---|---|---|---|
| direct answer | tool agent | w/o anatomy graph | + anatomy graph | |||
| Qwen3-VL-32B | 0.416 | 0.393 | 0.462 | 0.401 | 0.478 | 0.525 |
| GLM-5.3-Flash | 0.427 | 0.483 | 0.497 | 0.470 | 0.567 | 0.575 |
| InternVL3.5-38B (FP8) | 0.432 | 0.396 | 0.451 | 0.390 | 0.487 | 0.483 |
| MedGemma-27B | 0.404 | 0.309 | 0.393 | 0.377 | 0.414 | 0.433 |
| Claude Sonnet 5 | 0.445 | — | — | — | 0.513 | 0.553 |
Bold = best per row. — = not run. Accuracy on 903 multiple-choice questions; one sample per condition.
Paired comparisons (exact McNemar)
| Comparison | Qwen3-VL-32B | GLM-5.3-Flash | InternVL3.5-38B | MedGemma-27B | Claude Sonnet 5 |
|---|---|---|---|---|---|
| ClinicalEye vs 3DMedAgent | +6.3 (p=0.003) | +7.8 (p=1e-4) | +3.1 (n.s.) | +4.0 (p=0.07) | — |
| Single call: + anatomy graph vs without | +7.7 (p<0.001) | +9.7 (p<0.001) | +9.7 (p<0.001) | +3.7 (p=0.05) | — |
| ClinicalEye vs single call + anatomy graph | +4.7 (p=0.012) | n.s. | n.s. | n.s. | +4.0 (p=0.043) |
| ClinicalEye vs direct answer | — | — | — | — | +10.7 (p=1e-7) |
Differences in accuracy points. 3DMedAgent with benchmark metadata (organ / lesion / question type) removed, as in our protocol: Qwen 0.453, GLM 0.484, InternVL 0.464, MedGemma 0.391.
Calibration
The agent's expected calibration error is lower than that of the single call for 4 of 5 base models (e.g. Qwen3-VL-32B: 0.46 → 0.33).
Structure probes: can VLMs localise structures that have no tool?
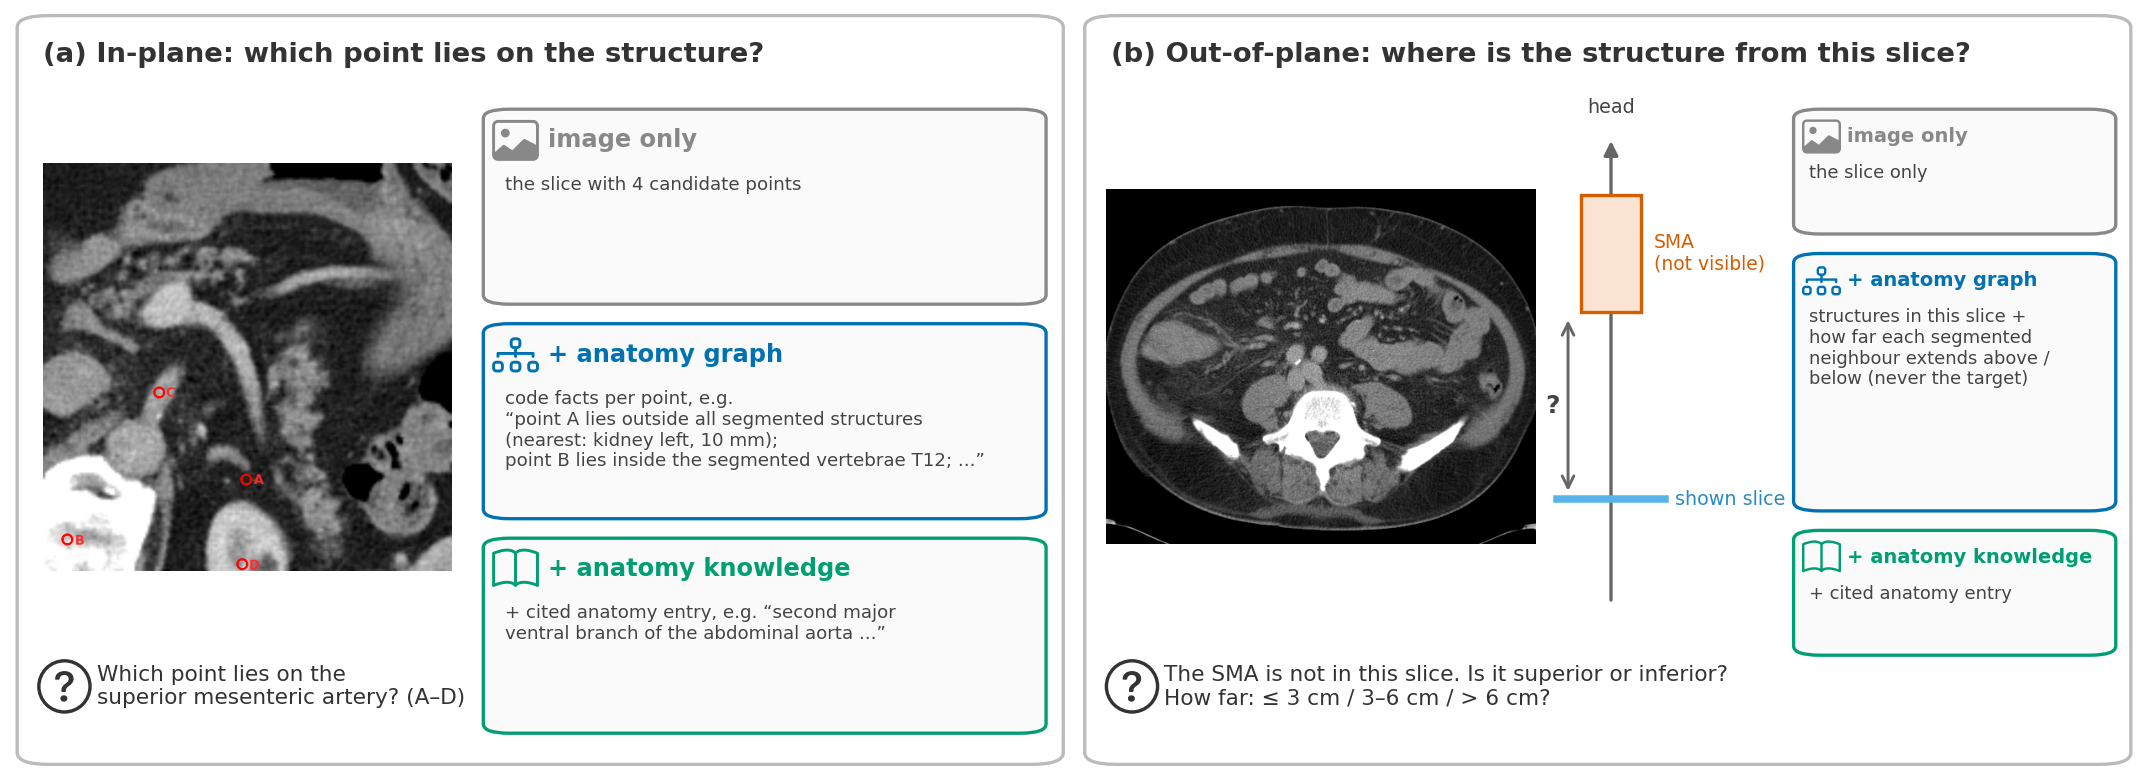
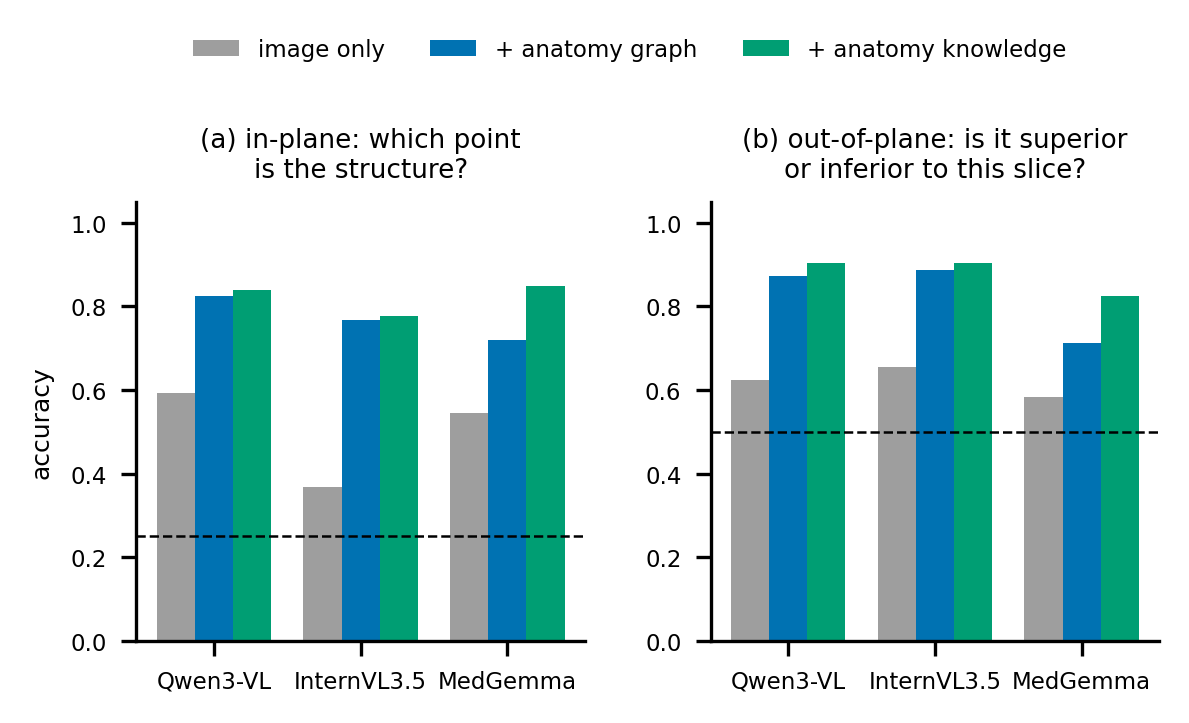
| Model | image only | + anatomy graph | + anatomy knowledge |
|---|---|---|---|
| In-plane: which of 4 points lies on the structure (125 items, chance 0.25) | |||
| Qwen3-VL-32B | 0.59 | 0.82 | 0.84 |
| InternVL3.5-38B | 0.37 | 0.77 | 0.78 |
| MedGemma-27B | 0.54 | 0.72 | 0.85 |
| Out-of-plane: superior or inferior to this slice (100 items, structures without a tool, chance 0.5) | |||
| Qwen3-VL-32B | 0.62 | 0.87 | 0.90 |
| InternVL3.5-38B | 0.66 | 0.89 | 0.90 |
| MedGemma-27B | 0.58 | 0.71 | 0.82 |
Distance estimation (3 bins: ≤3 cm / 3–6 cm / >6 cm) did not improve for any model.
Ablations (lite903)
Navigator (Qwen3-VL-32B)
| Setting | with navigator | without navigator | Δ | wins / losses | p |
|---|---|---|---|---|---|
| Pure views | 0.526 | 0.492 | +3.4 | +72 / −41 | 0.005 |
| Missing tool | 0.404 | 0.381 | +2.3 | +65 / −44 | 0.055 |
(a) To isolate the navigator's role in finding and explaining views, both variants are given pure views: the images contain only the CT, and all anatomical information reaches the reader as text. Removing the navigator costs 3.4 points (52.6 → 49.2, +72/−41, p=0.005).
(b) When the tool for the question's organ is missing (missing-tool setting), the agent with the navigator keeps more accuracy than without it (40.4 vs 38.1, +65/−44, p=0.055).
Replication on InternVL3.5 and MedGemma is running.
Memory and anatomy graph (Qwen3-VL-32B)
| Condition | Accuracy | Δ |
|---|---|---|
| Full ClinicalEye | 0.525 | — |
| w/o reader memory | 0.444 | −8.1 (p=5e-7) |
| w/o navigator memory | 0.519 | −0.6 (n.s.) |
| Single call w/o anatomy graph (vs single call, 0.478) | 0.401 | −7.8 (p<1e-4) |
Single call without the anatomy graph: −7.8 (47.8 → 40.1, p<1e-4).
Missing-tool simulation (single call)
The question's organ is removed from the segmentation (and from the graph, vocabulary, measurements and tool lesions), not from the images. Even the single call, which relies least on the tool, drops 5.4 points with Qwen3-VL (47.8 → 42.4, p=0.007) and 9.9 points with GLM (56.7 → 46.8, p<1e-6).
Takeaways
- Anatomy-graph facts are the main source of gain over published baselines with the same base models: a single call with the anatomy-graph summary already gains +3.7 to +9.7 pts; the full agent adds a further, significant gain only for Qwen3-VL-32B (+4.7) and Claude Sonnet 5 (+4.0).
- VLMs localise structures without a tool much better when given code-computed anatomy facts in text (in-plane 0.37–0.59 → 0.72–0.82; out-of-plane 0.58–0.66 → 0.71–0.89), with a further gain from cited anatomy knowledge.
- The navigator helps the reader understand what its views show (Qwen3-VL: +3.4 points with pure views, p=0.005; +2.3 when a tool is missing, p=0.055); the reader's memory matters most (−8.1).
- Limitations. Single sample per condition on a 903-question set. The navigator effect is moderate and so far measured on one model. Perception of lesions remains the bottleneck. Distance estimation does not improve with anatomy facts.